Column · @edwinvyqs041
Emergency Dentist Advice for Tooth Pain That Won’t Go Away
Tooth pain has a way of taking over everything. It steals sleep, ruins meals, shortens patience, and makes ordinary work feel far harder than it should. A mild ache that starts in the afternoon can become a throbbing, deep pressure by midnight. By the second or third day, people often stop asking whether they should get help and start asking how long they can hold out.
When pain does not settle, that question matters. Persistent tooth pain is not just a nuisance. It usually means something is inflamed, infected, cracked, or irritated in a way that your body cannot fix on its own. Sometimes the cause is relatively straightforward, such as a cavity that has reached the nerve. Sometimes it is more complicated, such as a cracked molar that hurts only when you bite and then progresses into constant pain. In either case, waiting too long tends to make treatment more invasive, more expensive, and less comfortable.
An Emergency Dentist sees this pattern every week. Patients often arrive after trying to push through a weekend, manage on over the counter pain relief, or hope the ache will “burn itself out.” Occasionally the pain does fade for a while, but that is not always good news. If a damaged tooth nerve dies, sharp pain may suddenly drop off, even as infection spreads beyond the tooth into the surrounding bone or gum tissue. That is one reason lingering or recurring pain deserves prompt attention, even if it briefly seems better.
Why lingering tooth pain rarely resolves on its own
A healthy tooth should not throb, stab, pulse, or ache for days. The structures inside a tooth are sensitive and confined to a very small space. When decay, trauma, or infection irritates the nerve, pressure builds quickly. Unlike a sore muscle, which may settle with rest, a tooth often continues to worsen because the source of irritation remains trapped.
Decay is one of the commonest causes. A small cavity might cause sensitivity to sweets or cold drinks. Once decay reaches deeper layers, the nerve becomes inflamed. At that point, pain can become spontaneous. It may wake you from sleep, worsen when you lie down, or linger long after eating or drinking. A filling might have solved the problem https://www.behance.net/smyledbakersf months earlier. Now the same tooth may need root canal treatment or extraction.
Cracks create a different kind of trouble. A cracked tooth may feel fine at rest, then give a sharp, electric pain when you bite into bread or chew meat. Because cracks can be tiny and hard to spot, people often delay care, thinking they simply “bit on it funny.” Over time, bacteria enter the damaged area and the pain pattern changes from intermittent to constant.
Gum and surrounding tissues also play a role. Food trapped around a wisdom tooth, an abscess near the root, or advanced gum disease can all produce significant pain that radiates into the jaw, ear, or temple. Patients are often surprised that a problem “in the gums” can feel like a severe toothache. That confusion is common, which is another reason a professional exam matters.
The signs that make this an emergency
Not every toothache requires a same hour appointment, but some symptoms should move you from “I’ll wait and see” to “I need urgent care.” The key issue is whether the pain is escalating, whether infection may be involved, and whether you are struggling to function normally.
Here are the situations that deserve prompt contact with an Emergency Dentist:
- swelling of the gum, face, or jaw
- pain that keeps you awake or is not controlled by standard over the counter medication used as directed
- fever, foul taste, pus, or bad breath that appeared with the tooth pain
- a broken, cracked, or knocked loose tooth after injury
- trouble opening your mouth, swallowing, or breathing
That last point is especially important. A dental infection can spread into deeper tissues. Difficulty swallowing, rapid swelling, or any sense that your airway is affected is not a wait until morning problem. It warrants immediate emergency medical attention.
There are also less dramatic situations that still should not sit for long. Pain triggered by hot drinks, sensitivity that lingers more than a few seconds, or discomfort when biting down on one specific tooth may not look urgent from the outside, but those are classic early warning signs of a deeper problem. The earlier you are seen, the more options you usually have.
What an Emergency Dentist is trying to figure out
Patients often expect the visit to focus only on pain relief. Pain control is part of the job, but the real goal is diagnosis. Tooth pain can be misleading. A patient may point to an upper molar when the actual issue is sinus pressure, or they may swear the lower left side hurts when a cracked upper tooth is referring pain down the jaw.
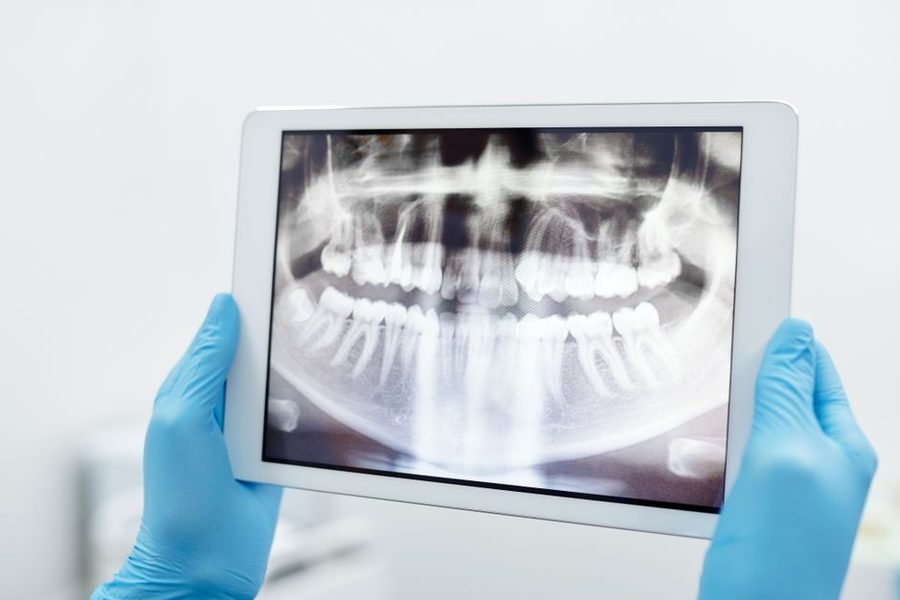
A careful urgent dental exam usually includes a conversation about when the pain began, whether it is triggered by cold, heat, pressure, or sweets, and whether it comes and goes or stays constant. The dentist may tap the teeth, check the gums, test temperature response, and take an X ray if needed. None of that is random. Each piece helps narrow the cause.
For example, pain that lingers after cold exposure often suggests nerve inflammation inside the tooth. Pain when releasing a bite can point toward a crack. Swelling over the root area may suggest an abscess. A deep cavity on X ray combined with spontaneous throbbing usually means the nerve is too compromised for a simple filling.
This matters because the right treatment depends on the source. Sometimes relief comes from draining an infection and starting definitive treatment quickly. Sometimes it means smoothing a sharp fracture, adjusting the bite, and planning a crown. Sometimes the best route is immediate extraction. The point is not to guess. It is to stop pain safely and preserve what can still be saved.
What you can do before your appointment
There is a sensible middle ground between ignoring tooth pain and trying every home remedy on the internet. Supportive care can make the hours before treatment more tolerable, but it should not replace assessment.
If you are waiting to be seen, stick to a short, practical plan:
- rinse gently with warm salt water a few times a day
- use over the counter pain medication only as directed on the packaging or by your clinician
- apply a cold compress on the outside of the cheek if swelling is present
- avoid very hot, very cold, sugary, or hard foods on the painful side
- keep the area as clean as possible with gentle brushing and flossing if tolerated
A few cautions are worth stating plainly. Do not place aspirin directly on the gum. It does not treat the tooth and can burn soft tissue. Avoid pressing clove oil, alcohol, or undiluted essential oils into the area, especially if the gum is irritated or open. If a filling or crown has fallen out, store it if you can find it, but do not force it back into place with glue from a hardware or craft kit. Temporary dental cement from a pharmacy may help in specific situations, but even then it is a brief stopgap, not treatment.
One practical detail many people miss is hydration. Pain, poor sleep, and difficulty eating often leave patients dehydrated and irritable, which makes everything feel worse. Sipping water and choosing soft foods like yogurt, scrambled eggs, soup that is not too hot, or mashed vegetables can make the wait more manageable.
Why painkillers can blur the real picture
A common pattern goes like this: the pain peaks, a patient takes ibuprofen or another over the counter medication, the pain backs off, and they decide the tooth is improving. Then it flares again the next day, often more aggressively. This cycle gives a false sense of progress.
Pain medication can reduce inflammation and interrupt the pain pathway, which is useful. It does not remove decay, close a crack, or drain an abscess. In fact, strong temporary relief can delay care long enough for the underlying problem to worsen. Dentists see this after holiday weekends all the time. A patient manages for two or three days, then arrives with facial swelling that was not there at the start.
Antibiotics are another point of confusion. They are not a cure for most toothaches. If the source is a dying nerve inside a tooth, antibiotics alone often do very little because the issue is trapped in a space with poor blood supply. An abscessed tooth usually needs dental treatment, such as root canal therapy, drainage, or extraction. Antibiotics may support that treatment when infection is spreading or swelling is present, but they rarely solve the problem by themselves.
Cases that seem minor but often are not
One of the trickiest categories is pain that appears only under certain conditions. A patient may say, “It only hurts when I chew nuts,” or “It only zings when I drink iced water.” Because the discomfort is not constant, they assume they have time. Sometimes they do have a short window, but these symptoms are often the earliest stage of a significant problem.
A tooth with a hairline crack may pass casual inspection and look intact in the mirror. Yet each bite flexes the fracture slightly, irritating the nerve. If left alone, that crack can deepen until part of the tooth breaks away. The eventual treatment moves from a crown to a root canal and crown, or even extraction, depending on the fracture line.
Another example is pain around a partially erupted wisdom tooth. It may come and go for months, especially after food gets trapped under the gum flap. People rinse, feel better, and move on. Then a more aggressive infection develops, often with swelling and reduced ability to open the mouth. Early evaluation could have prevented a miserable weekend and a more urgent procedure.
Teeth grinding is a quieter contributor. Nighttime clenching can inflame the ligament around teeth, create microcracks, and trigger morning soreness or headaches. Because there is no obvious cavity, patients are puzzled by the pain. A dentist can often distinguish this from infection by the pattern of tenderness, wear facets, and how the teeth respond during the exam.
What treatment may involve
When people hear “emergency appointment,” they sometimes imagine only a temporary patch. In reality, urgent dental care can range from immediate definitive treatment to a short stabilization visit, depending on the diagnosis, swelling, and how much time is available.
If the problem is decay that has not reached the nerve irreversibly, a filling may solve it. If the nerve is infected or inflamed beyond recovery, root canal treatment may be recommended to remove the damaged tissue and seal the tooth. For a tooth that is too broken down, deeply split, or severely infected, extraction may be the safer choice.
There are also in between measures. A dentist might open the tooth to relieve pressure, place a sedative dressing, recement a crown, smooth a fractured edge that is cutting the tongue, or drain a localized abscess through the gum. These steps are not cosmetic fixes. They can make an enormous difference in pain and help prevent complications while a full treatment plan is arranged.
Patients often ask which option is “best.” That depends on several factors: how restorable the tooth is, whether enough healthy structure remains for a long term restoration, how advanced the infection is, your general health, and your budget. Saving a tooth is usually desirable when the prognosis is sound, but there are cases where removing a badly compromised tooth is the most predictable route.
The role of timing in saving a tooth
Time matters more than most people realize. There is often a narrow period when a painful tooth is still salvageable with simpler treatment. Once infection spreads, decay deepens, or a crack travels below the gumline, options shrink.
Take a lower molar with a deep cavity. At first, the pain may be brief sensitivity to cold. A filling might have been enough. A few months later, the tooth starts throbbing at night. Now it may need root canal therapy and a crown. Wait longer, and the surrounding bone can become involved, leaving extraction as the only realistic answer. Same tooth, very different treatment, largely because of timing.
This is not about scaring people. It is about being honest about how dental disease behaves. Teeth do not heal like skin. Enamel does not knit itself back together. Once bacteria reach the inner tooth, the body can wall off infection for a while, but it rarely eliminates the source without treatment.
Children, older adults, and people with health conditions
Persistent tooth pain deserves even more caution in certain groups. Children may struggle to describe what they feel, so a serious problem can be dismissed as “teething” or sensitivity to sweets. If a child stops eating on one side, wakes at night crying with mouth pain, or develops swelling, they should be assessed promptly.
Older adults face a different set of issues. Exposed root surfaces, dry mouth from medication, old dental work, and gum recession all increase the risk of rapid decay and fracture. A crown that has been stable for fifteen years can loosen without much warning. Because pain perception may be altered by other health issues, the first obvious sign may be swelling or difficulty chewing rather than dramatic pain.
People with diabetes, immune suppression, recent chemotherapy, or certain heart conditions need prompt advice when dental infection is suspected. In these cases, what starts as a local dental problem can escalate more quickly and carry broader medical implications. That does not mean every toothache becomes dangerous, but it does mean delay is less wise.
How to choose where to go when it hurts now
Not every clinic handles urgent dental problems the same way. Some reserve same day slots specifically for emergencies. Others may fit patients in only for assessment and pain relief, with treatment booked afterward. If you are calling in pain, be clear about your symptoms. Mention swelling, fever, trauma, or difficulty sleeping. Those details help staff triage appropriately.
If you already have a regular dentist, call there first. They know your history and previous work. If you do not, look for a practice that specifically mentions emergency care and ask direct questions: Can you see severe tooth pain today? Do you treat infections, fractures, or lost crowns? What should I do if swelling worsens before the appointment?
A hospital emergency department can help when there is facial swelling, trauma, difficulty swallowing, or concern about a spreading infection, but it often cannot provide definitive dental treatment for the tooth itself. In many cases, you still need follow up with an Emergency Dentist as soon as possible.
The question patients ask most: can I wait one more day?
Sometimes yes. Often no. The safer answer depends on the pattern. Mild cold sensitivity without spontaneous pain might wait briefly if you have an appointment already scheduled. Constant throbbing, swelling, pain on biting, or a bad taste in the mouth should push you to act sooner. If the pain is keeping you from sleeping, eating, or concentrating, your body is telling you the problem has crossed out of the minor category.
One practical rule from clinical experience is this: if the tooth has been worsening over forty eight to seventy two hours, not improving, it is time to stop monitoring and get evaluated. That timeline is not a law of nature, but it is a useful threshold. Dental pain that persists and intensifies rarely rewards patience.
Tooth pain that will not go away is rarely random, and it is almost never best ignored. Prompt care does more than quiet the ache. It gives you the best chance of keeping the tooth, limiting infection, and avoiding a much bigger problem a few days from now. When pain starts to dominate your sleep, meals, or peace of mind, that is reason enough to call an Emergency Dentist and be seen.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.